
Most people who come to me about L5-S1 have already spent a few nights reading about it. The term might have appeared on a magnetic resonance imaging (MRI) report, next to words like “herniation” or “degeneration” that sound worse than they often are. Or a burning pain has started running down one leg, and a long drive or a meeting has become something you plan around. Either way, not knowing what the words mean for your life can feel heavier than the pain itself.
Quick Answer
What is L5 and S1? L5-S1 is the spot at the very bottom of your lumbar spine where your lower back connects to your pelvis and sacrum. It includes the fifth lumbar vertebra (L5), the top segment of the sacrum (S1), and the disc between them. Because this joint carries more body weight and bending stress than any other level of the lower back, it is one of the two most common places for a herniated disc, along with L4-L5.
The good news is that a finding at L5-S1 is a starting point, not a verdict. Where your pain travels, what makes it worse, and what your exam shows tell me a great deal about what is happening and what will help. Most people improve without surgery. My goal in this article is to explain the same things I explain to patients in my San Antonio and Houston offices, so the words on your report start to make sense.
Where Is L5 and S1 in Your Spine?
Your lower back has five lumbar vertebrae, numbered L1 through L5 from top to bottom. L5 is the last and the largest of them, built thick to carry the weight of everything above it. Just below L5 sits the sacrum, a triangle-shaped bone wedged between your hip bones, and S1 is its top segment. The L5-S1 disc is the cushion between these two bones, which makes it the lowest disc in your lumbar spine.
Quick Answer
Where is L5-S1 located? L5-S1 is located at the very bottom of the lumbar spine, where the lower back meets the pelvis and sacrum. L5 is the fifth and largest lumbar vertebra, S1 is the top segment of the sacrum, and the L5-S1 disc sits between them. The L5 and S1 nerve roots that travel down the leg pass through this area.
Doctors call this area the lumbosacral junction, because it is where the lumbar spine meets the sacrum. Above it, the lumbar spine curves and flexes every time you bend, twist, or lift. Below it, the sacrum is locked into the pelvis and moves very little. That meeting point absorbs a large share of the load and bending stress your back handles each day, which helps explain why disc problems show up here so often.
People sometimes ask whether they can find L5-S1 by touch. The two dimples in the low back sit near this level, but they are not precise landmarks, and the disc itself lies deep inside your body. A better way to picture it is that the L5-S1 disc sits at the very bottom of your lumbar spine, where your lower back connects to your pelvis and sacrum.
Two important nerves pass through this area. The L5 nerve root and the S1 nerve root both leave the spine near this level and travel down into your leg and foot. When something at L5-S1 presses on one of these nerves, the pain rarely stays in your back, and that is the clue we follow next
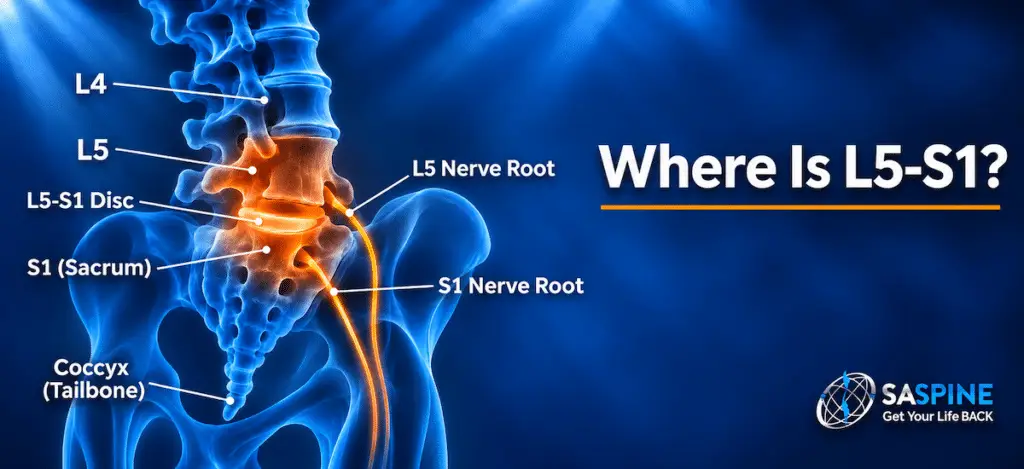
Knowing where L5-S1 sits turns a line on your MRI report into a place you can picture, and that picture is the first step toward understanding why it hurts.
Action Takeaway: Ask your doctor to point out L5 and S1 on your own images, so you can see which disc and which nerves your report describes.
What Does L5-S1 Pain Feel Like?
Pain from L5-S1 can show up in two different ways, and the difference matters for treatment. Some people feel a deep ache across the low back that gets worse with bending, lifting, or long periods of sitting. Others feel pain that travels down the leg, often called sciatica, along with numbness, tingling, or weakness. That traveling leg pain has a medical name, radiculopathy, and it means a spinal nerve root is being squeezed or irritated.
Quick Answer
What is the difference between L5 and S1 nerve pain? L5 nerve pain travels down the outer thigh and calf to the top of the foot and the big toe, and it can weaken your ability to lift the foot. S1 nerve pain travels through the buttock and the back of the thigh and calf to the outer foot and little toe, and it can weaken your ability to push off or stand on your toes. A neurological exam and imaging confirm which nerve is involved.
The location of pain in your legs and feet can tell us a lot about which nerve in your lower back may be compressed. When a patient tells me the numbness runs to the big toe instead of the little toe, that one detail already narrows the picture. This is the comparison I use during an exam:
| Finding | L5 nerve root | S1 nerve root |
|---|---|---|
| Pain or numbness | Outer thigh and calf, top of foot, big toe | Buttock, back of thigh and calf, outer foot and little toe |
| Weakness | Lifting the foot and extending the big toe; potentially foot drop | Pushing downward with the foot, standing on tiptoes |
| Examination | Heel walking, big-toe extension strength | Toe walking, Achilles tendon reflex |
| Sensory changes | Top of foot, especially the first webspace (the skin between the big toe and second toe) | Outer edge of foot and sometimes the sole |
These patterns overlap, and no two people fit a chart perfectly. That is why I confirm the diagnosis with a neurological examination and imaging rather than relying on symptoms alone.
At L5-S1, which nerve gets pinched depends on where the disc pushes out. A herniation in the center of the spinal canal, or just off center, most often presses on the S1 nerve root. A herniation that pushes into the opening where a nerve leaves the spine, called the foramen, or farther out to the side, can press on the L5 nerve root instead. A very large central herniation can press on several nerve roots at once. The location of the herniation is just as important as the spinal level.
Many people with an L5-S1 disc problem also notice that sitting makes their leg pain worse. That pattern is common with disc problems, and it is worth mentioning at your appointment.
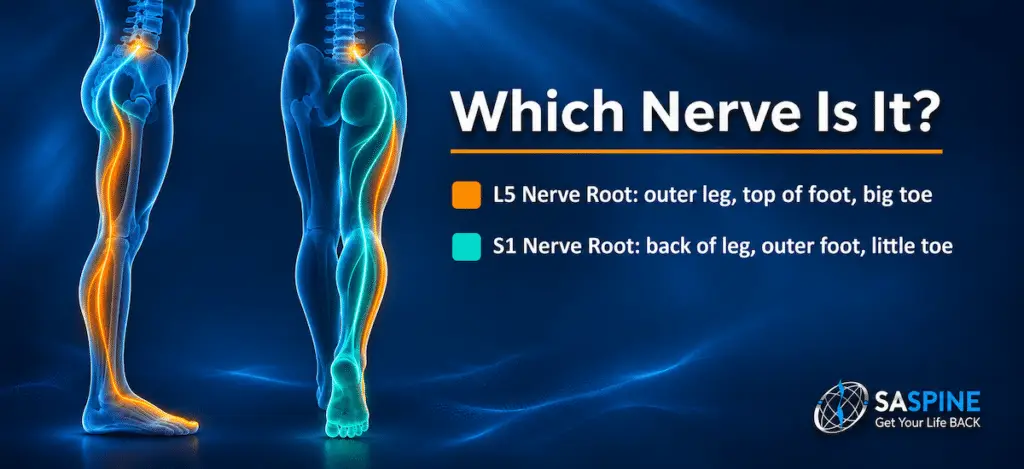
Your symptoms are information, not only discomfort, and describing them clearly gives your doctor a head start.
Action Takeaway: Before your visit, write down exactly where your pain, numbness, or weakness travels, down to which toes, and bring that note with you.
What Causes Problems at L5-S1?
Knowing which nerve is irritated answers half of the question. The other half is what is pressing on that nerve, and at L5-S1 a handful of causes account for most of what I see in my practice.
Quick Answer
What causes L5-S1 pain? The most common causes of L5-S1 pain are a herniated or bulging disc, degenerative disc disease (age-related disc wear), spondylolisthesis (a forward slip of L5 on S1, often from a pars fracture), and spinal stenosis. Repeated heavy lifting and twisting, long hours of sitting, smoking, and extra body weight can add strain to this level over time.
Herniated or bulging disc. Each intervertebral disc has a tough outer ring and a softer center. With wear or a sudden strain, part of the center can push through a tear in the outer ring and press on a nerve. A disc bulge is a broader, milder version of the same problem. L4-L5 and L5-S1 are the two most common levels for a lumbar disc herniation, according to the American Academy of Orthopaedic Surgeons, and our team offers herniated disc treatment that ranges from therapy to surgery.
Degenerative disc disease. As we age, discs lose water and height. Despite the name, degenerative disc disease is age-related disc wear rather than a disease in the usual sense, and many people have it on imaging without any pain. When a worn disc does cause trouble, it can lead to back pain, bulging, and narrowing around the nerves.
Spondylolisthesis. Spondylolisthesis means one vertebra has slipped forward on the one below it. At L5-S1, the slip often starts with a stress fracture in the pars interarticularis, a small bridge of bone at the back of the vertebra. A pars fracture can begin in the teen years, especially in young athletes who arch their backs over and over, and it can let L5 slip forward on S1 with time. The American Academy of Orthopaedic Surgeons explains spondylolysis and spondylolisthesis in more detail, and you can see how spondylolisthesis is corrected in surgery. Degenerative spondylolisthesis, a slip caused by wear in the facet joints, can also occur at this level.
Spinal stenosis. Stenosis is a narrowing of the space around the nerves, often from thickened ligaments, bone spurs, and worn facet joints. If stenosis is part of your picture, my article on newer treatments for spinal stenosis walks through the options by stage.
Some habits and conditions add strain to this level over time, including repeated heavy lifting and twisting, long hours of sitting, smoking, and extra body weight. None of these guarantees a problem, and many people develop L5-S1 changes without any of them, but each one is worth knowing about.
Most of these causes develop slowly, which is why they often respond well to patient, well-planned care. A few situations, though, cannot wait.
Action Takeaway: Ask your doctor which cause your imaging points to, because the cause, not the level alone, decides which treatments make sense.
When Is L5-S1 Pain an Emergency?
Most L5-S1 problems give you time to learn, ask questions, and try conservative care. A small number do not. The bundle of nerves at the bottom of your spinal canal, called the cauda equina, controls your bladder, your bowels, and sensation in the groin area, along with strength in your legs. A large disc herniation can compress that bundle, a condition called cauda equina syndrome, and it needs treatment right away.
Quick Answer
When is L5-S1 pain an emergency? Go to the emergency room right away if back or leg pain comes with new trouble urinating, loss of bladder or bowel control, numbness in the groin or inner thighs, or leg weakness that is new or getting worse. These can be signs of cauda equina syndrome, which needs urgent treatment to prevent permanent nerve damage.
Go to the emergency room now if you notice any of these:
- New trouble starting to urinate, being unable to empty your bladder, or holding urine
- New loss of bladder or bowel control
- Numbness in the groin, genitals, inner thighs, or around the anus, sometimes called saddle numbness
- New or fast-worsening leg weakness, including foot drop
- New severe symptoms in both legs, especially with weakness or changes in bladder, bowel, or saddle sensation

Please do not wait until you lose complete control of your bladder or bowels. Early signs of cauda equina syndrome can be subtle, and delays in diagnosis and surgery to relieve the pressure can lead to permanent nerve damage. The American Association of Neurological Surgeons describes this condition and why speed matters. If something feels wrong, being checked and reassured is always the better choice.
See a doctor promptly for these symptoms, even when they are not an emergency:
- Back pain with fever, chills, or other signs of infection, which can point to a spinal infection
- Unexplained weight loss, pain at night that will not ease, or a history of cancer along with new back pain
Knowing these signs lets you relax about the rest, because without them, time is on your side.
Action Takeaway: Save this list on your phone or share it with a family member, so someone close to you knows what to watch for.
How I Treat L5-S1 Problems Without Surgery
Without those warning signs, the outlook is encouraging. Most people with an L5-S1 disc herniation and leg pain get better without surgery, and my first job is to give the body the right conditions to heal.
Quick Answer
Can an L5-S1 herniated disc heal without surgery? Yes, in most cases. About 75 to 90 percent of people with back pain or a herniated disc improve with 6 to 12 weeks of the right conservative care, such as activity changes, physical therapy, and medication. Some herniated discs shrink on their own over time. Worsening weakness or emergency symptoms need a specialist’s evaluation right away.
I tailor the order of care to each patient, but it tends to follow these steps:
- Activity changes. Avoid what makes the leg pain worse while staying as active as you comfortably can. Long periods of bed rest slow recovery rather than help it.
- Medication. Anti-inflammatory medicines such as ibuprofen or naproxen can ease pain and inflammation if they are safe for you. Check with your doctor before starting any new medication.
- Physical therapy. A targeted physical therapy program builds flexibility, core stability, and better movement habits without irritating the nerve.
- Epidural steroid injection. An image-guided injection places anti-inflammatory medicine near the irritated nerve. It can calm pain for a period of time, but it does not remove the herniated disc.
- MRI and a specialist visit. Imaging and a spine surgeon’s opinion make sense when symptoms do not improve, weakness develops, or we need a clearer picture to plan treatment.
Many patients begin to feel better within the first several weeks, with larger gains over 6 to 12 weeks. Some herniations shrink through a natural process called spontaneous resorption, which takes pressure off the nerve. Less pain does not always mean the nerve has fully recovered, though, so I keep watching strength and sensation along with pain.
While an L5-S1 disc heals, I ask patients to avoid:
- Heavy lifting
- Repeated forward bending
- Twisting while carrying weight
- Sitting for long stretches without breaks
- High-impact activities
- Aggressive stretching that makes nerve pain worse
Walking as tolerated is one of the best things you can do for yourself during this time. For more ideas you can use at home, see my guide to ways to relieve sciatica pain.
Conservative care is not “doing nothing.” It is a plan with steps, checkpoints, and a clear point at which we reconsider the approach.
Action Takeaway: Set a check-in with your doctor about six weeks into conservative care, so your plan has a clear moment to measure progress.
When Does L5-S1 Need Surgery?
For a smaller group of patients, conservative care does not bring enough relief, or the nerve shows signs of real damage. Surgery then becomes part of the conversation, and the decision comes down to matching the right procedure to the right problem.
Quick Answer
When does an L5-S1 herniated disc need surgery? Surgery is considered when disabling leg pain continues after about 6 to 12 weeks of good conservative care, especially when an MRI shows nerve compression that matches your symptoms. Earlier surgery may be the right choice for severe pain that does not respond to treatment, significant or worsening weakness, or suspected cauda equina syndrome. The procedure depends on what is causing the compression.
Time alone does not decide it. I weigh your symptoms, your neurological exam, your imaging, how much the problem limits your daily life, and the expected benefits and risks of surgery. The right procedure is determined by the underlying problem rather than by the presence of pain alone.
- Microdiscectomy removes the piece of herniated disc pressing on a nerve, through a small incision. Microdiscectomy is the procedure I use most for a disc fragment compressing a nerve root.
- Laminectomy or other decompression removes bone or thickened tissue to make more room for nerves squeezed by stenosis. You can read more about laminectomy and how it is performed.
- Lumbar fusion joins two vertebrae so they heal into one solid bone. Lumbar fusion is considered when there is significant instability, deformity, or another structural problem that needs stabilizing, such as some cases of spondylolisthesis.
- Artificial disc replacement replaces a worn disc with an implant that preserves motion. I am trained in both cervical and lumbar disc replacement, and it can fit carefully selected patients with symptomatic degenerative disc disease who have not improved with conservative care and meet specific criteria. It is not the right choice for everyone.
When surgery is on the table, I will evaluate your condition, explain each option along with its advantages and potential drawbacks, and tell you why I am recommending one approach over another. That way, you can make an informed decision about your own care.
“The most important factor in treating an L5-S1 condition is identifying the actual source of pain or nerve dysfunction and choosing the treatment that addresses that specific problem, not simply treating what appears abnormal on an MRI.” Steven Cyr, M.D., F.A.A.O.S.
A good surgical plan answers one question clearly: what is pressing on which nerve, and which procedure addresses that specific problem.
Action Takeaway: If surgery is recommended, ask your surgeon what is causing the compression and why the chosen procedure fits that cause better than the alternatives.
What Does Recovery Look Like?
Whether you heal with conservative care or surgery, recovery unfolds in stages. How long it takes depends on your condition, the treatment, your overall health, and how physical your daily life is, so the ranges below are general estimates rather than fixed rules.
Quick Answer
How long is recovery from L5-S1 treatment? With conservative care, most people return to normal or modified activity in about 4 to 8 weeks. After a microdiscectomy, desk work often resumes in 2 to 4 weeks, with full activity around 3 months. After a lumbar fusion, desk work resumes in about 4 to 12 weeks, and heavy physical work can take 6 to 12 months. Nerve recovery is often slower than pain relief.
| Treatment | Desk work | Light to moderate physical work | Heavy labor | Full activity and restrictions |
|---|---|---|---|---|
| Conservative care | As symptoms allow | Gradual return in 4 to 8 weeks | Gradual return in 4 to 8 weeks | Most improve in 6 to 12 weeks |
| Microdiscectomy | 2 to 4 weeks (light duty sometimes 1 to 2) | 4 to 6 weeks | 6 to 12 weeks, often with work changes | Full activity and sports around 3 months |
| Lumbar fusion | 4 to 12 weeks (one level vs. several) | 3 to 6 months | 6 to 12 months, or a permanent job change | No bending, lifting, or twisting for the first 6 weeks to 3 months |
Heavy work takes longer for a reason. After a microdiscectomy, the outer wall of the disc needs time to heal. After a fusion, the bone graft and hardware need time to become solid, which is why bending, lifting, and twisting are off limits early on.
Nerve recovery is often slower than pain relief, especially when the compression was severe or long-standing. Many patients notice their leg pain easing soon after surgery, while numbness or weakness takes considerably longer to improve. That gap is normal, and it is one reason follow-up visits matter.
Early after surgery, avoid long, unbroken stretches of sitting. Change positions often and take short walks through the day, with breaks about every 20 to 30 minutes at first. Do not drive while you are taking sedating pain medication, or if weakness, pain, or stiffness could affect your control of the car. After an uncomplicated microdiscectomy, many patients drive again within days to a few weeks, while after a fusion it can take several weeks or longer.
Recovery also asks something of you mentally. Progress rarely moves in a straight line, and a stiff morning after a good week can feel discouraging. I encourage patients to look at the overall direction rather than any single day, and to stay steady with walking, therapy, and their activity limits.
Action Takeaway: Ask for a written recovery plan with your activity limits and return-to-work timeline, so you and your employer can plan ahead.
Next Steps
L5-S1 problems are common, and most of them improve. The path forward starts with clear answers to two questions: which nerve is involved, and what is pressing on it. Once those answers are in hand, the right treatment becomes much easier to choose, and the fear that comes with an unfamiliar diagnosis tends to ease.
If you are living with low back or leg pain, or you have an MRI report that mentions L5-S1, I would be glad to review it with you. Schedule a visit with me at our San Antonio office at 11459 Huebner Road, (210) 487-7463, or our Houston office at 9125 West Road, Building B, (832) 919-7990. If you have had a previous MRI, please send a digital copy ahead of time or bring it to your first appointment, so we can look at it together.
Frequently Asked Questions
Is an L5-S1 herniated disc serious?
+Can an L5 and S1 disc heal without surgery?
+What should I avoid with an L5-S1 disc problem?
+Can L5 and S1 cause pain in both legs?
+Is walking good for L5-S1 pain?
+

Our Comprehensive Guide
Authored by Steven Cyr, M.D., F.A.A.O.S., Chief Medical Officer and Surgeon at SASpine, this essential guidebook offers valuable insights into managing back pain effectively. Download your complimentary copy today and take the first step towards a pain-free life!
Send download link to:



